Asynchronous Telehealth vs Live Video Visits for Skin Concerns
Asynchronous reviews work best for stable conditions.
The average wait for a nonurgent dermatology appointment runs 36.5 days. For most patients, the real decision is expert attention this week through a screen versus expert attention next month in an exam room. That gap in timing is what's actually pushing people toward telehealth, far more than any excitement about apps or video calls. And because the two formats aren't interchangeable, picking one without understanding what it can and cannot do means patients may be choosing comfort over fit.
What store-and-forward and live video do, structurally
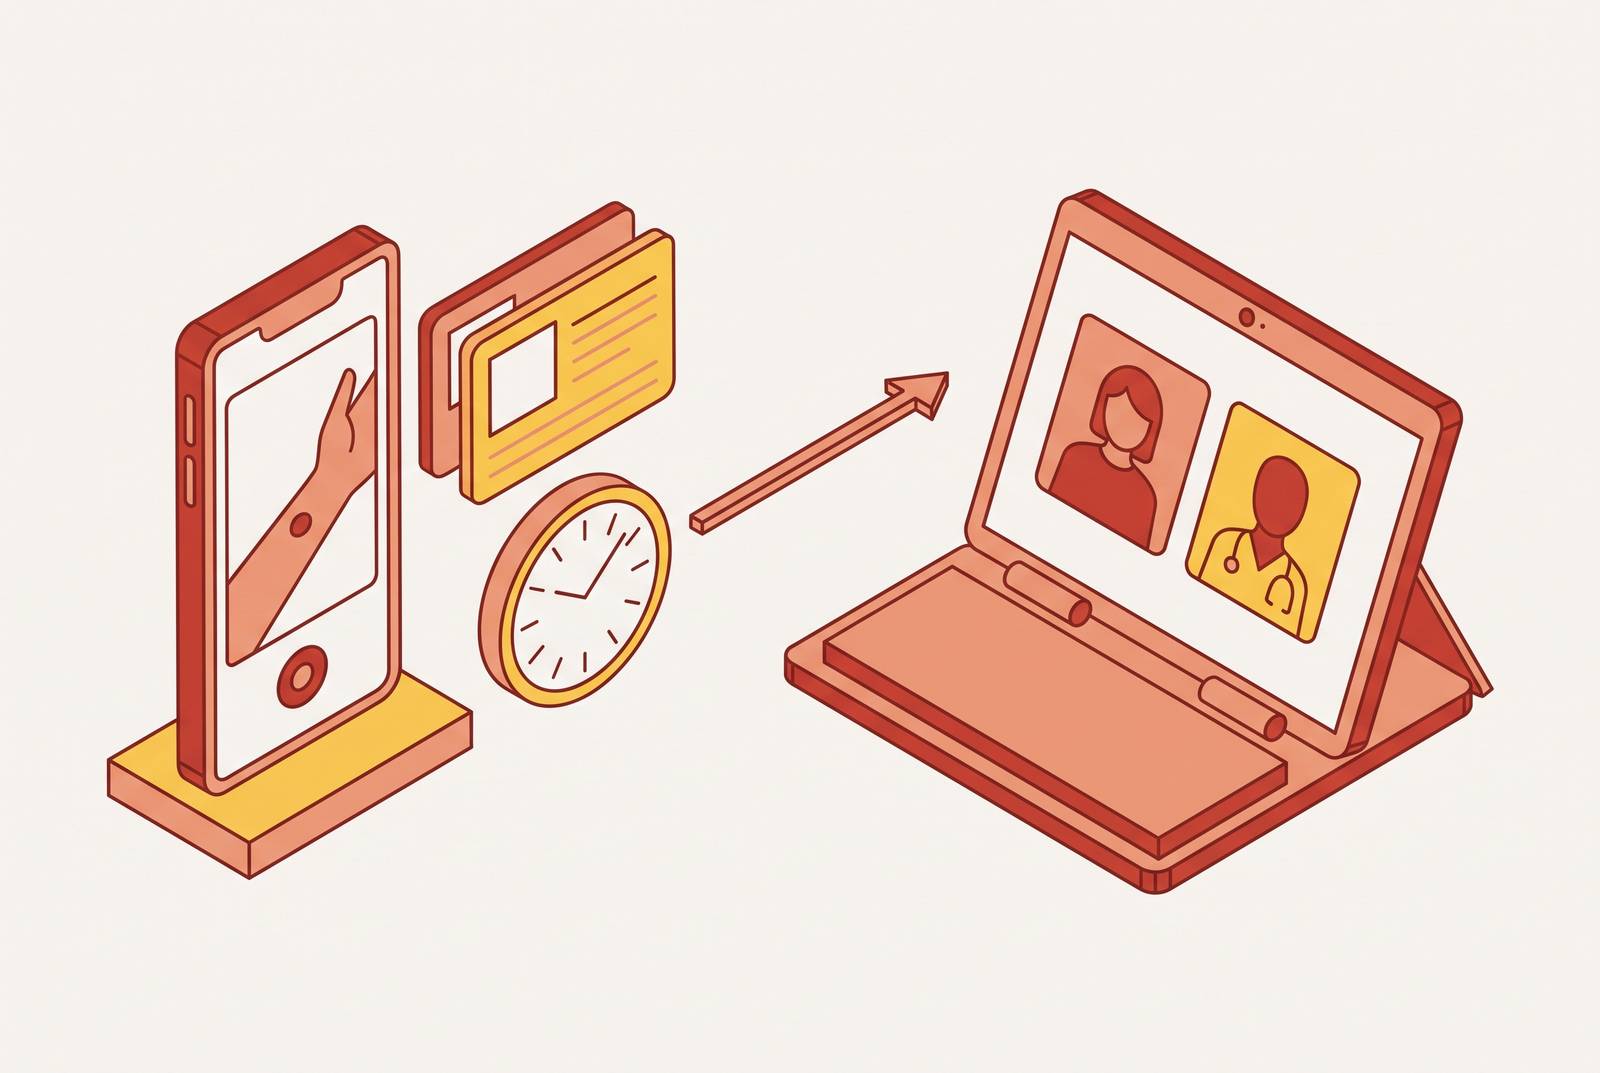
Store-and-forward and live video solve the same basic problem, getting a dermatologist's eyes on a patient's skin, through two different mechanical processes. In store-and-forward, sometimes called asynchronous telehealth, a patient submits high-resolution photos along with a written history, and a clinician reviews the file independently, often hours later. Neither side needs to be online at the same time. That separation in timing is what makes the format efficient: an AMA case study found a dermatologist can complete an asynchronous consult in a fraction of the time a live visit takes. Because skin conditions are visual by nature, and a sharp still photo often captures more diagnostic detail than a compressed video stream, store-and-forward has become the dominant model in teledermatology.
Live video works on a different logic. The patient and clinician are present together in real time, over two-way audio and video. That live connection lets the clinician direct the exam as it happens, asking the patient to turn toward the light, pull back a sleeve, or hold still for a closer look. The tradeoff is image quality: video compressed over a typical home internet connection frequently delivers less clinical detail than a single well-lit photograph. Even so, live video remains the format patients reach for most. A cross-sectional study of 2,064 teledermatology encounters found that video-only visits made up the majority of the dataset, which suggests live video is the more familiar choice for patients, even when it isn't the more informative one for the clinician.
A third model blends the two: a patient submits photos ahead of time, then joins a live video call to walk through them with the clinician. The same 2,064-encounter study found that how often this hybrid approach gets used, versus video-only, varies meaningfully depending on the condition being evaluated. The variation signals that the condition itself, not habit or convenience, should be driving which format a visit takes.
Which skin conditions each format handles well
The question of which format fits which concern comes down to what a clinician actually needs to see or do in order to make a call. Some conditions are read almost entirely from a photograph: color, texture, distribution across the body. Others require real-time direction, a biopsy tool, or a conversation that unfolds rather than one written down in a form.
Store-and-forward does well with conditions defined by visual appearance over time. Acne, eczema, psoriasis, general rashes, and moles or spots that have stayed stable all fall into this category, since the clinical picture lives in color, shape, and spread rather than in texture felt by hand. Hair and nail conditions also tend to fit this model well, since pattern and extent across the scalp or nail bed matter more for diagnosis than watching the condition unfold in real time. Follow-up visits and routine medication management are a natural fit too, since the clinical question is usually narrow and the history is already documented. The 2,064-encounter study bears this out directly: inflammatory conditions made up nearly half of all teledermatology encounters, with acneiform conditions and lesions following behind.
The UPMC experience makes the case concrete. Its e-Derm and e-Consult platforms handle non-scarring alopecia, conditions like androgenetic alopecia, alopecia areata, telogen effluvium, and traction alopecia, entirely asynchronously. Under e-Consult, referring providers send clinical histories and photographs to a dermatologist for review across the UPMC network; under e-Derm, patients submit directly themselves. A 2025 retrospective study found this model effective at reaching patients who otherwise had limited access to dermatologic care. Nobody needed a live camera, a real-time conversation, or a trip to an office. A photo and a history were enough.
Live video earns its place where a still photo falls short. A patient who can't easily photograph their own back or scalp benefits from a clinician who can direct the angle and lighting in the moment. Some concerns are also easier to explain out loud, like when a rash started, what triggered it, or what other symptoms came with it, than to summarize on an intake form. And when a rash is changing fast, live video lets a clinician gauge urgency on the spot rather than wait for a photo to arrive.
Neither format, though, replaces a physical exam. Biopsies, cryotherapy, injections, and a full-body skin check with dermoscopy all require tools and hands-on contact that no camera can substitute for. Telehealth extends the reach of a diagnosis and a treatment plan, but it does not turn a procedure into something that can happen through a screen, a point many patients misunderstand going in. A lesion that's bleeding or changing by the day calls for an in-person visit.
How diagnostic accuracy holds up across formats
Virtual dermatology often holds up well against seeing a doctor in person, but not evenly across every condition or every photo submitted.
A comparison of store-and-forward against live interactive video found kappa coefficients, a statistical measure of agreement, ranging from 0.41 to 0.63 when matched against in-person diagnosis. That range lands in moderate-to-good agreement, not a perfect match, but a real one. A broader literature review on PubMed reached a similar conclusion: most studies show high accuracy and strong diagnostic concordance between teledermatology and in-person assessment, with that accuracy improving further when teledermoscopy, magnified imaging of the skin, gets added to the mix.
The variable that actually swings these numbers is image quality, not format. A 2025 randomized cohort study published in the International Journal of Telemedicine and Applications found that giving patients brief training on how to photograph their own skin improved diagnostic outcomes. In other words, how a patient frames, lights, and focuses a photo shapes what a clinician can conclude from it, sometimes as much as the underlying condition does.
That finding cuts two ways for store-and-forward. Its reliance on patient-submitted photos is the same thing that makes it efficient and the same thing that makes it risky. A sharp, well-lit image lets a clinician work almost as if they were in the room. A blurry or poorly framed one limits what any amount of clinical skill can extract from it. Live video offers a partial fix, since the clinician can coach the patient through getting a better angle or better lighting in real time, but compressed video over an ordinary home connection introduces its own ceiling on detail.
None of this means one format beats the other across the board. Accuracy depends on the pairing of format and condition. The evidence is strongest for inflammatory and acneiform conditions, the rashes and breakouts that read clearly from a good photo, and less settled for lesions, where fine texture and surface detail carry real diagnostic weight and a camera, however good, can only approximate what a hand and a dermatoscope pick up directly. What a patient submits, and how carefully, shapes what a clinician can actually see and conclude from it.
What AI contributes to virtual skin assessment
AI pattern recognition has become part of how a lot of asynchronous platforms work, flagging likely conditions, sorting cases by urgency, and speeding up what a clinician reviews first. But two limitations, well documented and not yet resolved, keep AI in a supporting role rather than a replacement one: bias tied to skin tone, and the risk of clinicians trusting a wrong prediction too readily.
Bias is the more serious of the two limitations. Most AI models built to detect skin lesions were trained on datasets made up overwhelmingly of light-skinned patients. That training gap produces a measurable drop in performance: one study found a sharp drop in diagnostic accuracy for Black skin conditions compared to Caucasian images, using an AI dermatology tool trained on Caucasian datasets. This is a structural problem built into the data these tools learned from, and it hasn't been fixed across the commercial tools on the market.
The second limitation is subtler and appears in how clinicians use AI output rather than in the AI itself. Research published in Nature Medicine in 2026 found that as an AI system's accuracy drops, physicians become more likely to fold its incorrect predictions into their own diagnosis. That risk climbs highest on the hardest cases, including images of dark skin. The exact patients already underserved by biased training data are also the ones most likely to be hurt twice over, once by a weaker model, and again by a clinician who trusts that weaker output more than they should.
AI also struggles with the same practical issues that limit any photo-based review: brightness, contrast, blur, stray hair, skin markings, and unusual body locations all degrade how well these systems perform. Taken together, these limits are why the evidence-based model treats AI as a complement to a clinician's judgment that supports rather than replaces diagnostic decisions. AI cannot yet cover the full range of skin conditions, its reasoning isn't always clear enough to audit, and its equity gaps remain open. The responsible setup uses AI for triage and pattern-flagging, while a board-certified dermatologist or licensed clinician makes the actual call. Platforms built on large, labeled clinical datasets, reviewed actively by clinicians and tested against different skin tones on an ongoing basis, represent that model in practice.
How telehealth format affects access equity
AI bias is one version of a bigger truth: format choice has consequences that reach well past one patient's convenience. Telehealth genuinely widens the door to dermatologic care for people who face real obstacles getting into an exam room. But that widening is not automatic or evenly distributed, and the same features that expand access for one patient can leave another just as stuck.
Start with what telehealth removes. Transportation costs, time off work, and simply living far from a dermatologist are concrete barriers that asynchronous care sidesteps. An AMA case study of Asian Health Services found that most patients using its teledermatology program never needed a follow-up in-person visit at all, a meaningful win for anyone juggling transportation limits or an inflexible work schedule. Asynchronous care also removes the scheduling overlap that live visits require. Neither side has to be free at the same moment, which matters most for shift workers and anyone caring for someone else on a tight schedule.
Those gains come with a catch. Reliable internet, a smartphone good enough to produce a usable clinical photo, and enough comfort with the technology to use it all are not resources every patient has equally. Geographic licensing rules add another layer: a dermatologist can typically only see patients in the states where they're licensed, so someone in a state with few licensed telehealth dermatologists faces a narrower set of options than someone in a well-served one. Closing one access gap, in other words, can open another one if the rollout isn't handled with care.
Cost runs through all of this too. Teledermatology visits tend to cost meaningfully less per patient than in-person ones, with telehealth charges often running well below in-person visit charges, which makes format as much a financial decision as a clinical one. Even a modest, message-based consult with a real licensed clinician beats a delayed appointment or no care at all, and affordability shapes format choice as much as which condition is being treated.
Medicare adds its own layer of complexity. Part B covers telehealth dermatology for visual, problem-focused visits, a new rash, a mole photo, a medication follow-up, but not procedures. The rules around this coverage have shifted repeatedly through 2025, extended first through March 31 and then through September 30, with ongoing uncertainty about what comes after. Anyone relying on Medicare for a dermatology telehealth visit should confirm coverage before booking, since the policy has shifted repeatedly through 2025, including the March 31 and September 30 extensions.
Sources
- Medicare Telehealth Dermatology Coverage in 2025 Guide
- Use of hybrid versus video-only teledermatology varies by condition: A cross-sectional study of 2064 encounters
- Teledermatology: Comparison of Store-and-Forward Versus Live Interactive Video Conferencing
- Clinical Case Study: Telehealth for Dermatology
- Teledermatology Diagnostic Accuracy: A Randomized Cohort Study Comparing Three Image Acquisition Techniques - Saade - 2025 - International Journal of Telemedicine and Applications - Wiley Online Library
- Store-and-Forward Teledermatology for Assessing Skin Cancer in 2023: Literature Review